Ophthalmology · Grand Rounds
Clinical Case Presentation
Title of Case
Bilateral pellucid marginal degeneration with cortical cataract: intraocular lens power selection in extreme against-the-rule astigmatism
A woman in her late 50s with three years of progressive, painless diminution of vision in both eyes — and a cornea that defies the biometer.
+8.51 D
ΔK · Right Eye
+10.90 D
ΔK · Left Eye
6/36 · 6/18
BCVA with contact lens RE · LE
Cornea & Cataract Services · Tertiary Eye Care Centre
Presented by Rohan Sonawane
02 · Summary02 / 23
The case in 150 words
A woman in her late 50s presented with three years of painless, progressive diminution of vision in both eyes, right worse than left. Corrected acuity was 2/60 and 4/60 with high compound myopic against-the-rule astigmatism. Slit-lamp examination revealed bilateral inferior peripheral corneal thinning sparing the limbus, without vascularisation or ulceration, together with cortical cataract in both eyes. Tomography and anterior segment optical coherence tomography confirmed bilateral pellucid marginal degeneration. Biometry showed keratometric astigmatism of +8.51 D and +10.90 D. A semi-scleral contact lens trial improved vision, confirming the corneal contribution. Cataract surgery of the right eye was planned with a monofocal intraocular lens, with power selection guided by the Barrett Universal II formula and a planned staged approach to the residual irregular astigmatism.
2
Pathologies per eye — ectasia + cataract
Combined surgical problem
3 yrs
Painless progressive visual decline
Near and distance
53.36 D
Steepest keratometry recorded
Right eye · K2 @ 174°
Pellucid Marginal Degeneration · Cortical CataractBMJ Case Report Structure
03 · Background03 / 23
Why this case matters
- Pellucid marginal degeneration is a rare, idiopathic, non-inflammatory ectatic disorder — a crescentic band of inferior peripheral corneal thinning, classically 1–2 mm from the limbus, with the point of maximal protrusion above the band of thinning.
- The topographic signature is the “crab-claw” pattern: inferior steepening with flattening of the vertical meridian, producing severe against-the-rule astigmatism.
- Presentation is usually in the 2nd–5th decade with slowly progressive blurring; pain, photophobia or hydrops are uncommon.
- When PMD coexists with visually significant cataract, every step of cataract surgery becomes contested territory: keratometry is unreliable, formulas disagree, and toric or multifocal lenses may harm rather than help.
- This case illustrates a reasoned pathway — confirm the ectasia, prove the corneal contribution with a contact lens trial, then plan lens power and refractive target conservatively.
Non-inflammatory Peripheral Corneal EctasiaBackground
04 · Case Presentation — History04 / 23
Three years of quiet decline
Three years before presentation
Apparently well, then noticed diminution of vision in both eyes, right worse than left — for both near and distance.
Course
Gradually progressive and painless — no redness, watering, photophobia, or history of trauma.
At presentation
Vision inadequate for daily activities despite spectacles; referred to a tertiary eye care centre.
Relevant negatives
- Past illness — no history of any systemic disease.
- Previous operations — no history of any ocular surgery.
- Allergies — none reported.
- Family history — no similar complaints in the family; no eye rubbing or atopy elicited.
History — Anonymised per BMJ GuidanceCase Presentation
05 · Case Presentation — Examination05 / 23
Systemically well; visually crippled
General physical examination
| General health | Good; afebrile; no pallor |
| Pulse / Resp | 78 /min · 16 /min |
| Blood pressure | 145/88 mm Hg |
| Random glucose | 7.9 mmol/L (142 mg/dL) |
| Systemic exam | Cardiovascular, respiratory, gastrointestinal and nervous systems grossly within normal limits |
Visual acuity & refraction
| Right eye | Left eye | |
|---|---|---|
| Unaided (distance) | 1/60 | 3/60 |
| With spectacles | 2/60 | 4/60 |
| Best accepted refraction | −2.0 DS / −7.5 DC × 90° → 4/60 | −1.0 DS / −9.0 DC × 90° → 5/60 |
| BCVA with contact lens | 6/36 | 6/18 |
| Near (with +1.5 add) | N8 | N6 |
| Pattern | Compound myopic against-the-rule astigmatism, both eyes | |
Acuity Refractory to Spectacle CorrectionCase Presentation
06 · Case Presentation — Anterior Segment06 / 23
Slit-lamp: a thinning band, a quiet eye
Right eye
| Cornea | Inferior thinning 3–8 o'clock, 1 mm inside the limbus; clear cornea above; tram-track lipid deposition at the edge; no vascularisation, no ulceration |
| Ant. chamber | Deep (Van Herick 4), regular; no cells or flare |
| Iris / pupil | Brown, no neovascularisation; 2→8 mm, central, brisk |
| Lens | Cortical cataract (worse than left); visual axis involved on retro-illumination |
| IOP | 19 mm Hg |
Left eye
| Cornea | Inferior thinning 3–6 o'clock, sparing the limbus; lipid deposition at the edge; no vascularisation, no ulceration |
| Ant. chamber | Deep (Van Herick 4), regular; no cells or flare |
| Iris / pupil | Brown, no neovascularisation; 2→8 mm, central, brisk |
| Lens | Cortical cataract; vitreous clear |
| IOP | 15 mm Hg |
Both Corneas: Ectatic, Uninflamed, UnvascularisedCase Presentation
07 · Clinical Photographs — Right Eye07 / 23
The cornea in profile
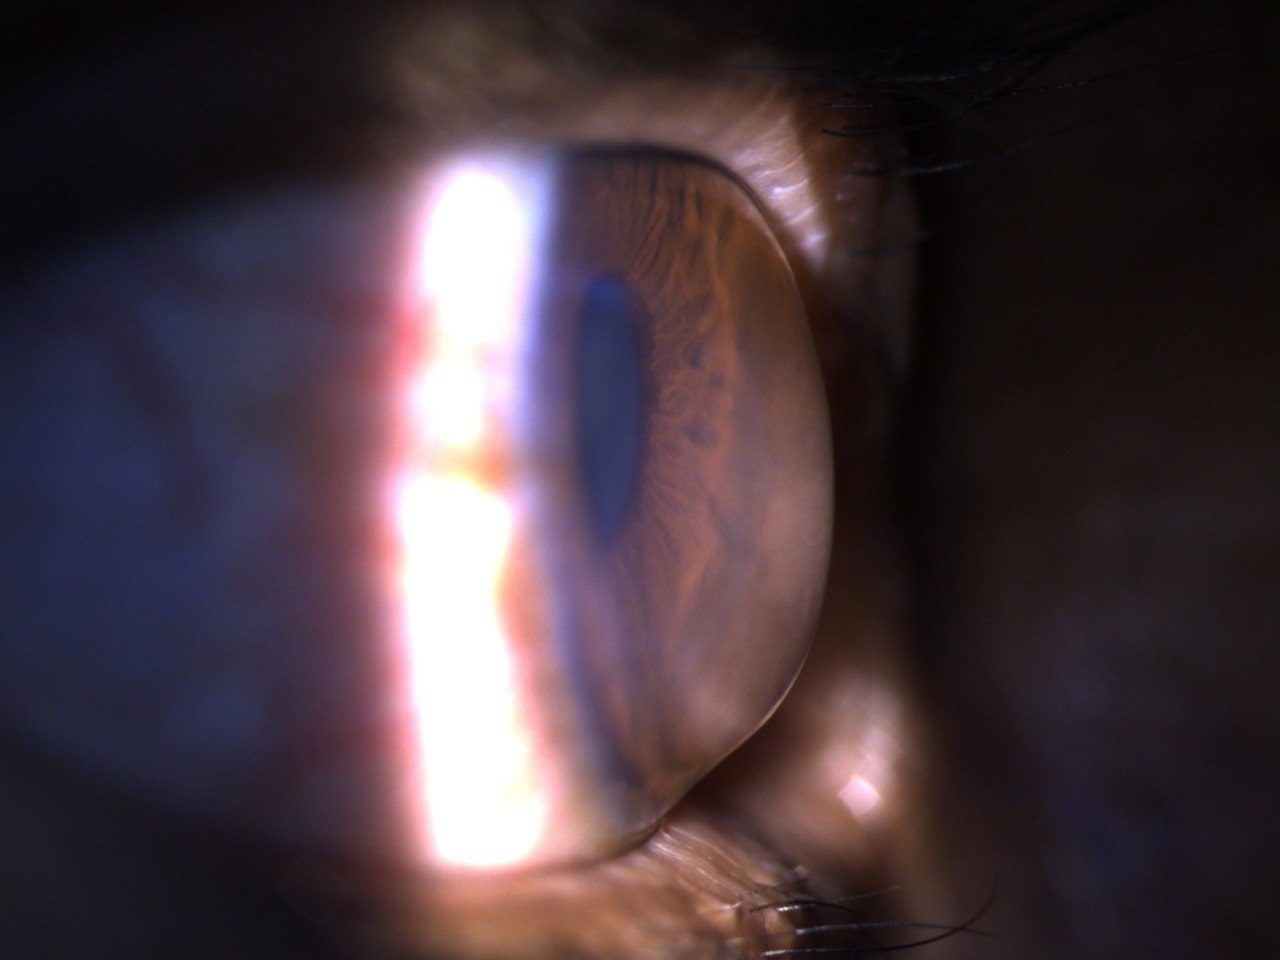
Right eye · 01
Inferior peripheral thinning
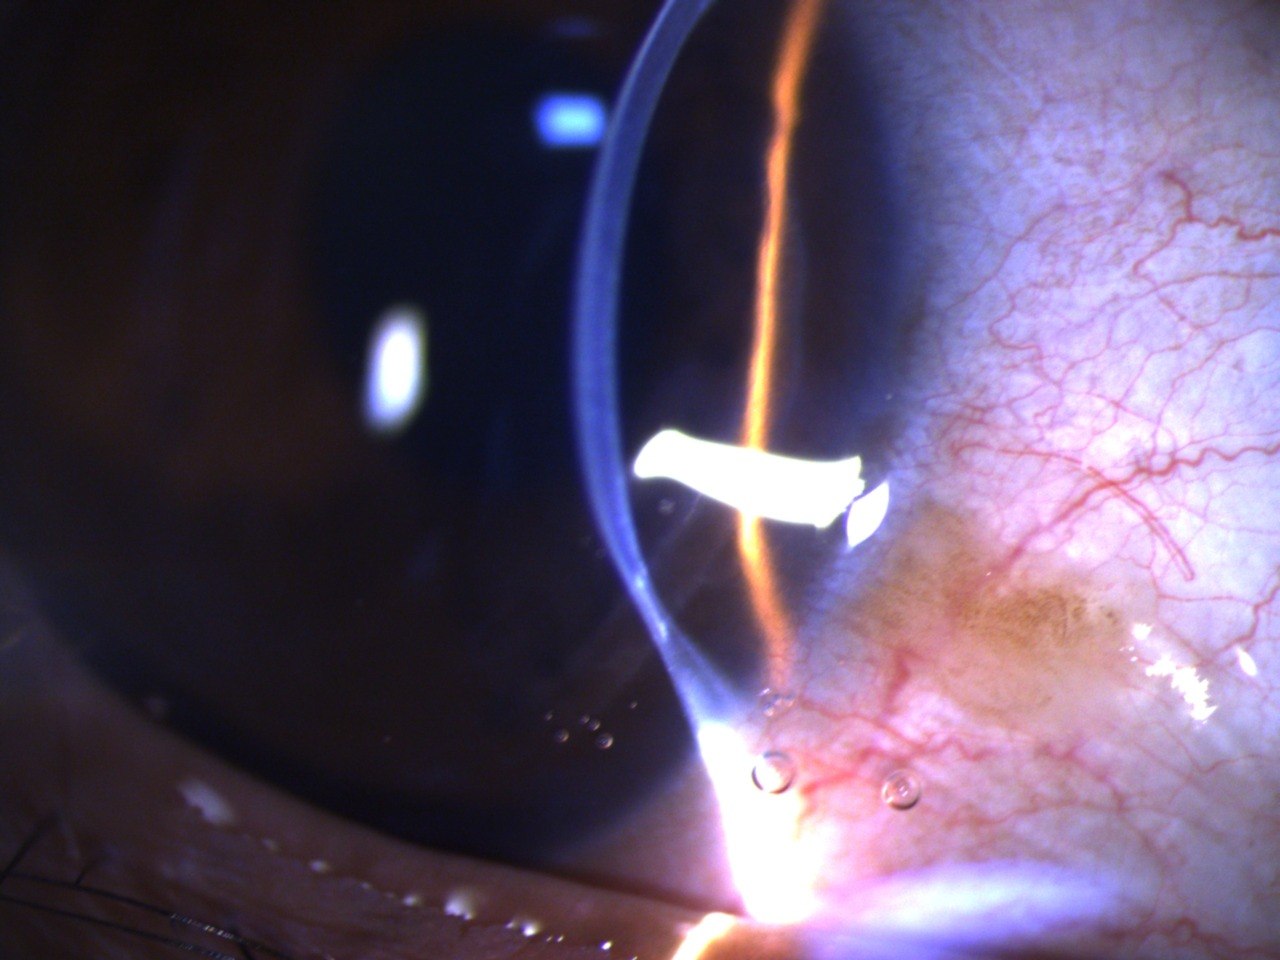
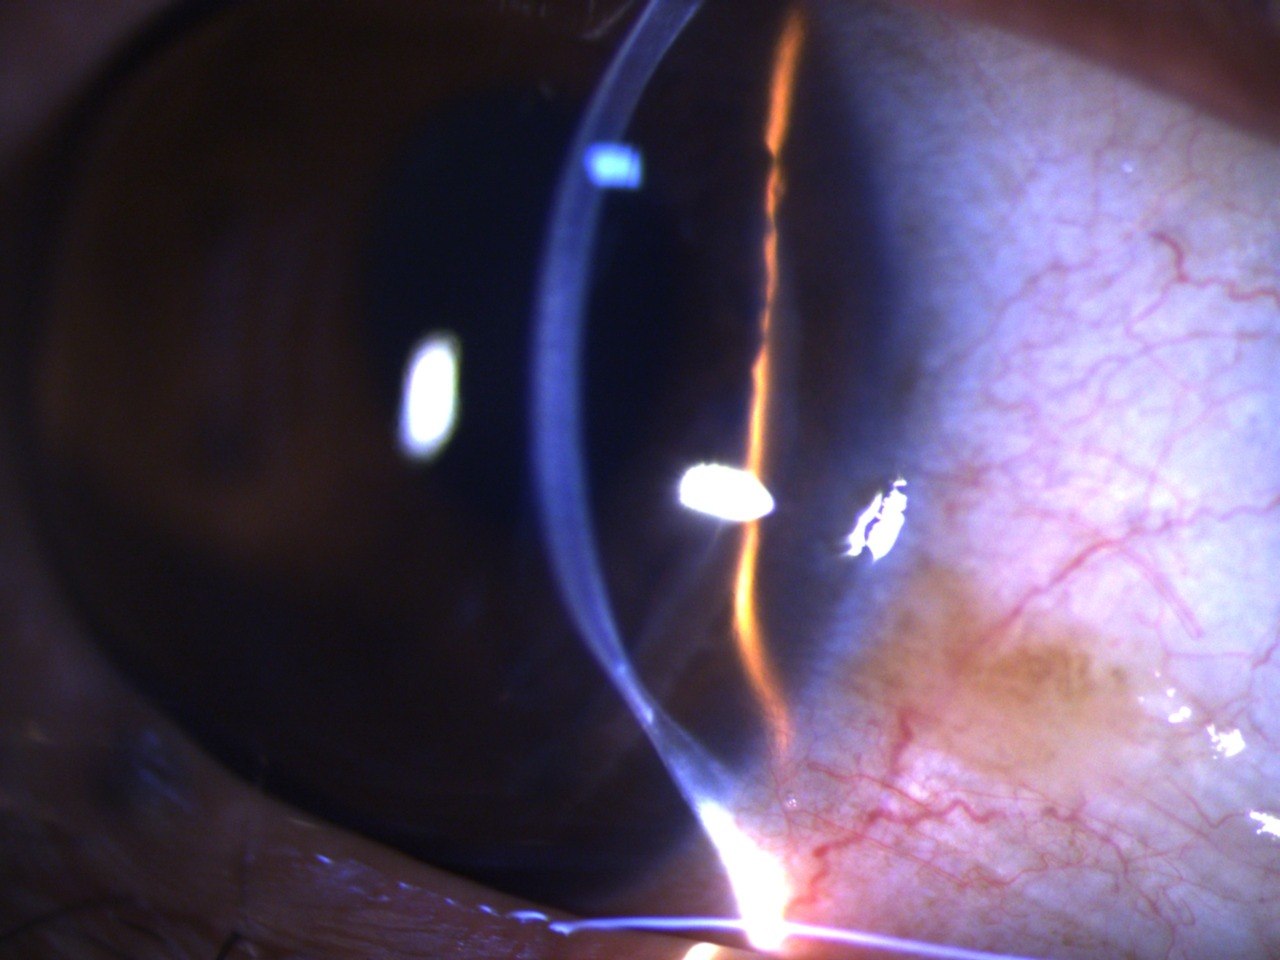
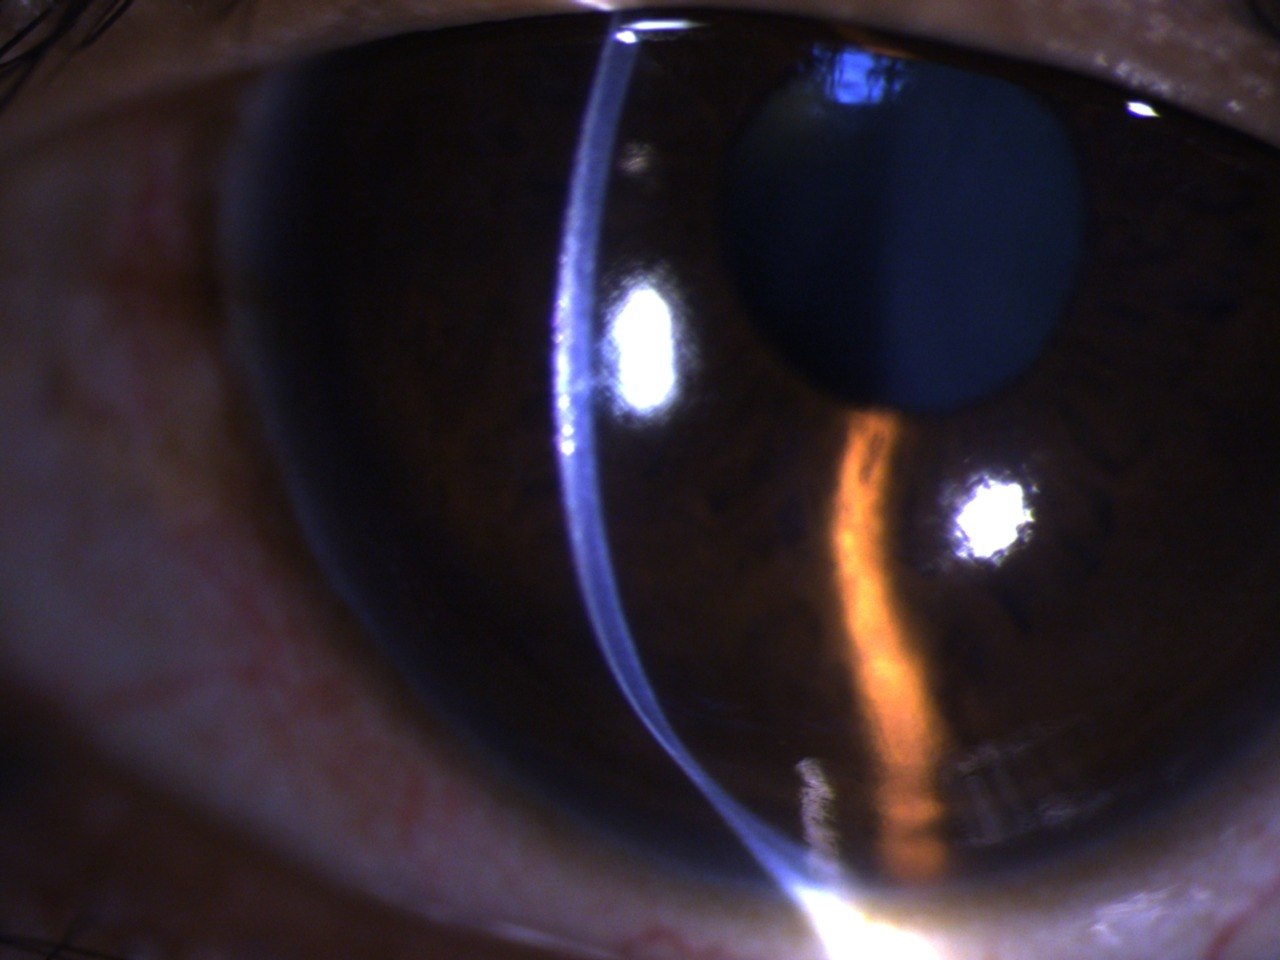
Broad optic section across the inferior cornea — the section narrows toward the periphery while the cornea above stays clear.
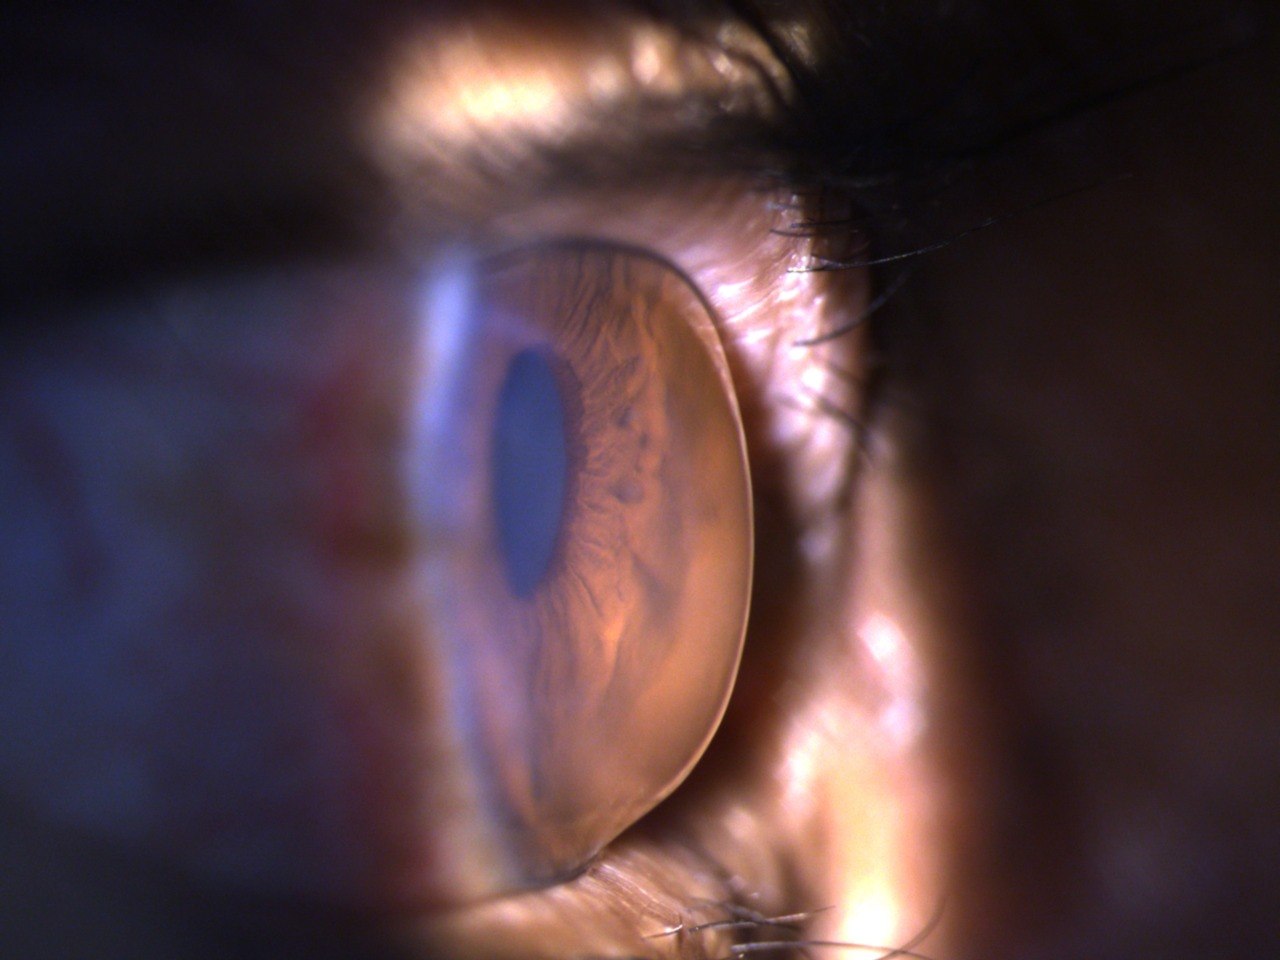
Right eye · 02
Tangential view — the contour bows forward above the thinned band.
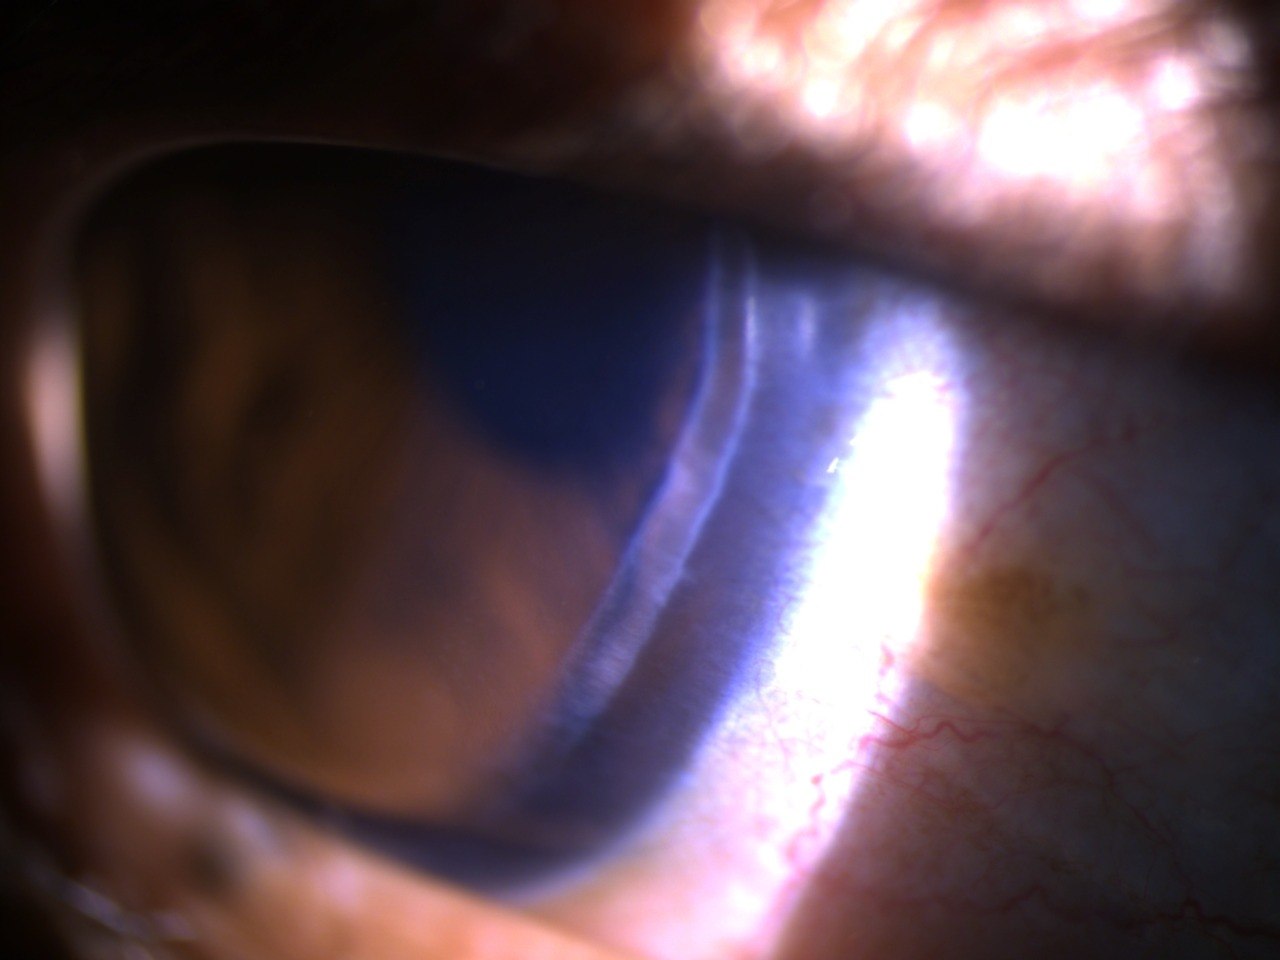
Right eye · 07
Inferior periphery — thinning band inside a clear limbus.
What to look forA crescent of thinning 1 mm inside the limbus, 3–8 o'clock, with clear cornea above it — no vascularisation, no infiltrate.
Slit-lamp Photography · Right EyeClinical Photographs
08 · Clinical Photographs — Right Eye, Detail08 / 23
Periphery, limbus, and lens
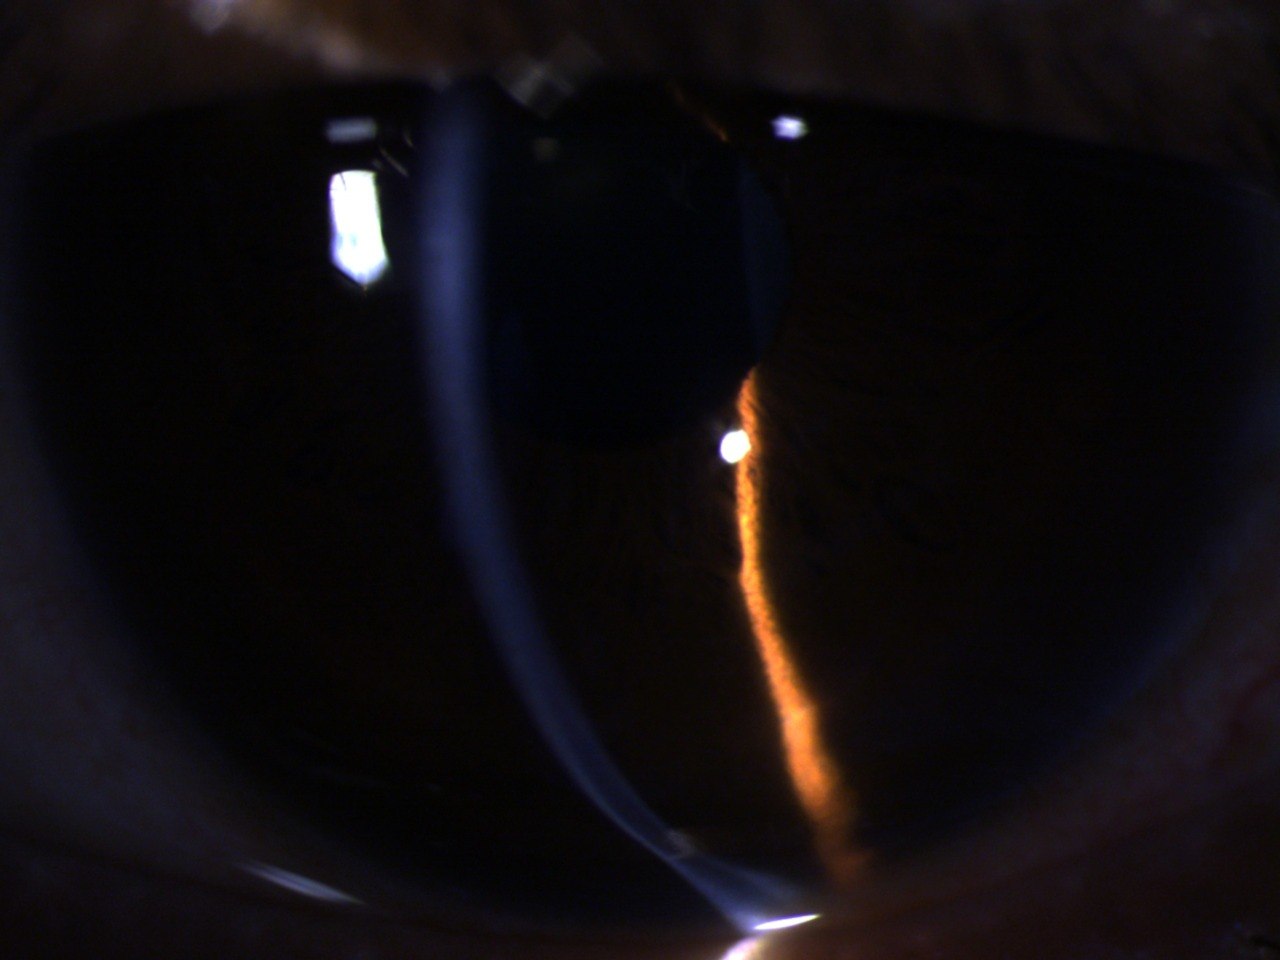
03
Optic section crossing the inferior cornea.
08
Peripheral section — the beam narrows toward the limbus.
09
Adjacent section — thinning stops short of the limbus.
04
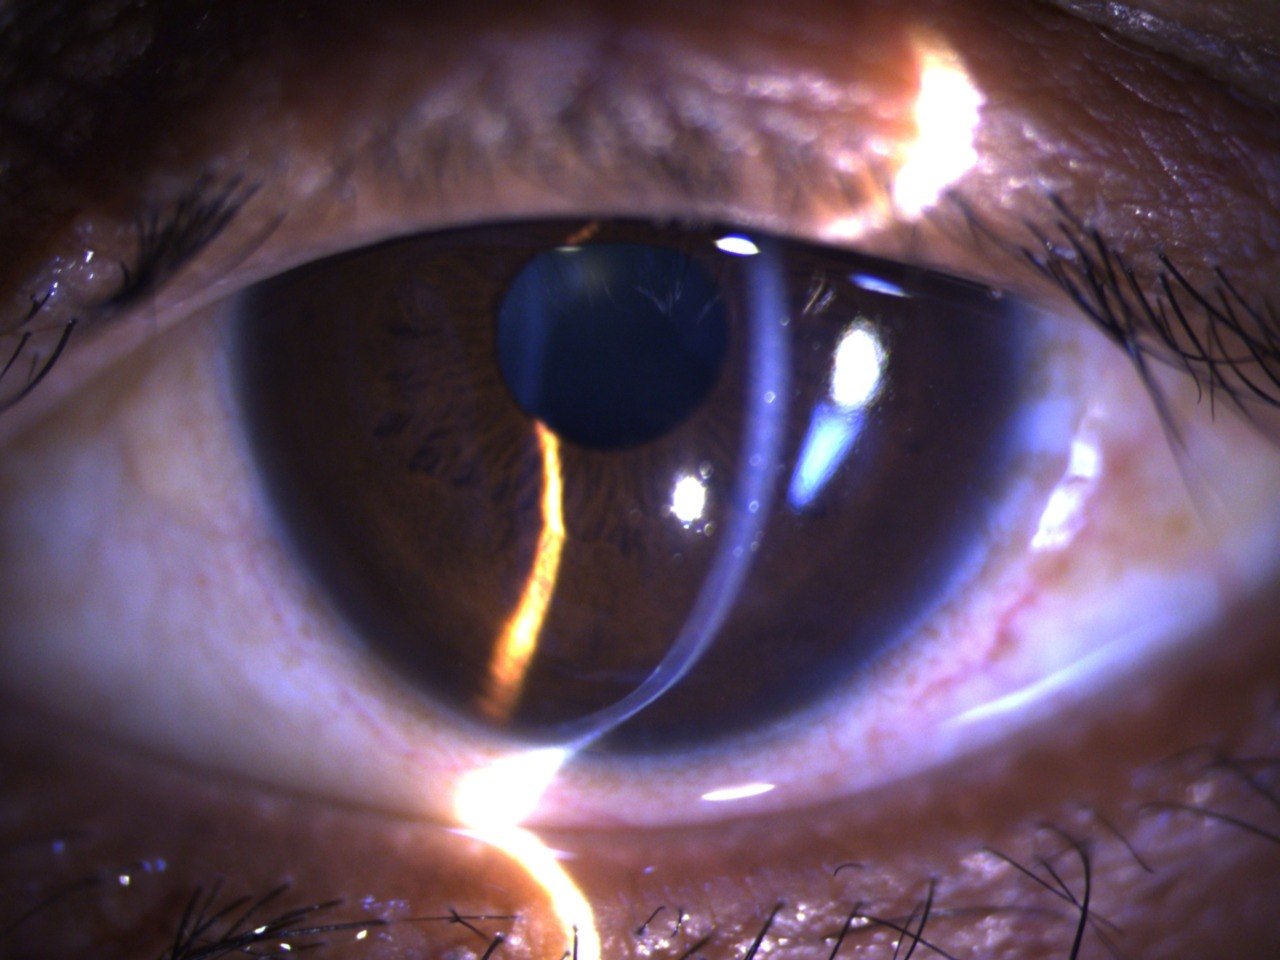
Diffuse view with section through the pupil.
05
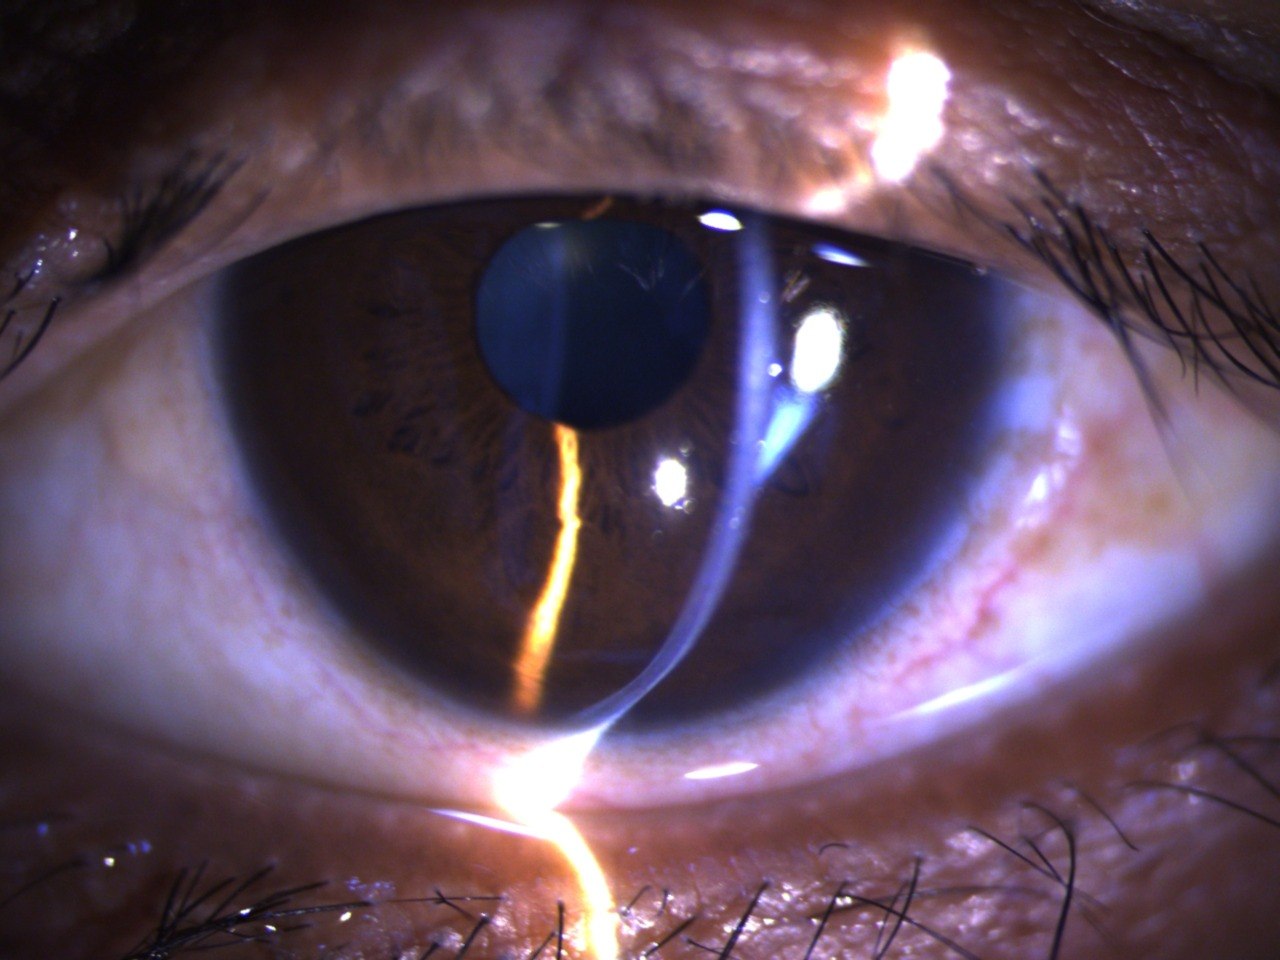
Section through the lens — opacity on the visual axis.
06
Higher magnification — cortical cataract in the pupillary area.
Two Pathologies in One Eye: Ectasia and CataractClinical Photographs
09 · Clinical Photographs — Left Eye09 / 23
The fellow eye, one step behind
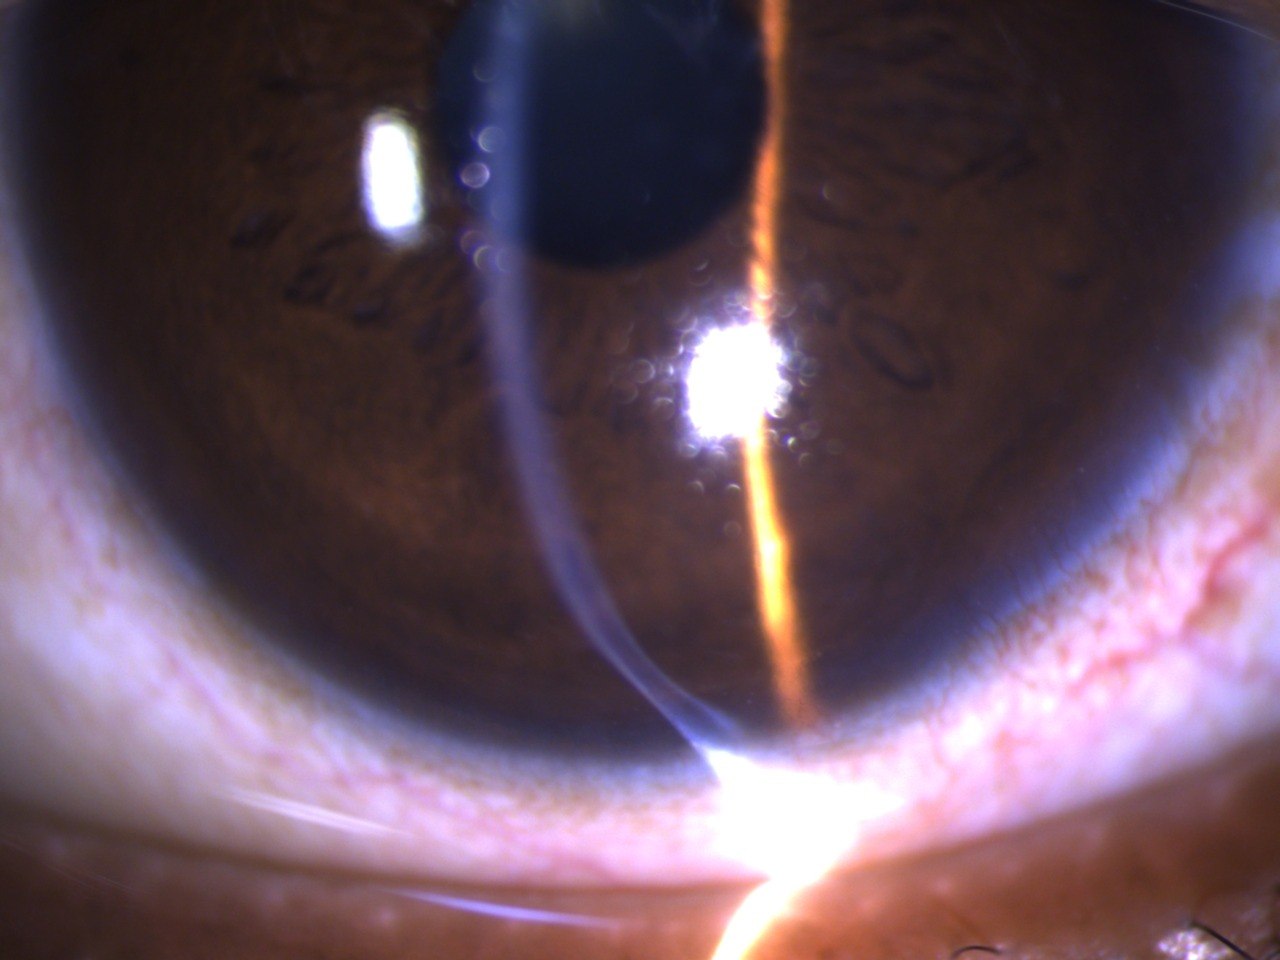
Left eye · 10
Inferior thinning, 3–6 o'clock
Optic section through the inferior cornea and pupil — the same crescent of peripheral thinning, over a cortical cataract.
Left eye · 10Thinning spans a shorter arc than the right — 3–6 o'clock, sparing the limbus, with lipid deposition at the edge of the band.
6/18
Best-corrected acuity with contact lens
Right eye 6/36
15 mm Hg
Intraocular pressure
Right eye 19 mm Hg
+10.90 D
Keratometric astigmatism, ΔK @ 5°
Worse than the right eye
Bilateral, Asymmetric — Left Eye Less AdvancedClinical Photographs
10 · Case Presentation — Posterior Segment10 / 23
The fundus of a myopic eye
- Media — clear beyond the cataract; good fundal glow both eyes.
- Discs — cup–disc ratio asymmetry: recorded 0.5 : 0.3 on initial dark-room examination and 0.9 : 0.5 on dilated glaucoma evaluation with peripapillary atrophy — prompting a formal glaucoma workup.
- Retina — dull foveal reflex; extensive chorioretinal degeneration in both eyes; arteriovenous ratio 1:2; an inferior pigmented lesion in the left eye, flat, without fluid.
Glaucoma-suspect workup
- Prior glaucoma clinic registration retrieved.
- Gonioscopy — open angles, posterior trabecular meshwork visible; iris processes noted.
- Humphrey visual fields 30-2 ordered both eyes; topical ocular hypotensive therapy initiated per glaucoma service.

Gonioscopy · 01

Gonioscopy · 02
GonioscopyOpen angle with the posterior trabecular meshwork in view; iris processes bridge the recess.
Disc Asymmetry + Myopic Degeneration Shape the PrognosisCase Presentation
11 · Investigations — Corneal Imaging11 / 23
Confirming the ectasia
- Scheimpflug tomography (Pentacam) — inferior steepening with the classic crab-claw pattern; maximal protrusion above the thinning band; both eyes affected, asymmetrically.
- Anterior segment OCT (radial scans) — band of inferior peripheral stromal thinning with preserved central thickness; epithelium intact throughout; thinnest peripheral pachymetry ≈ 377 µm against a central ≈ 483 µm.
- Macular OCT — performed to exclude macular pathology contributing to visual loss before surgical planning.
2280 · 2673
Specular endothelial count, cells/mm² (RE · LE)
Adequate for phacoemulsification
6/36 · 6/18
Best-corrected acuity with contact lens, right and left
Confirms corneal contribution · predicts rehabilitation
Tomography + ASOCT + Specular Microscopy + CL TrialInvestigations
12 · Investigations — AS-OCT, Right Eye12 / 23
The thinning, measured
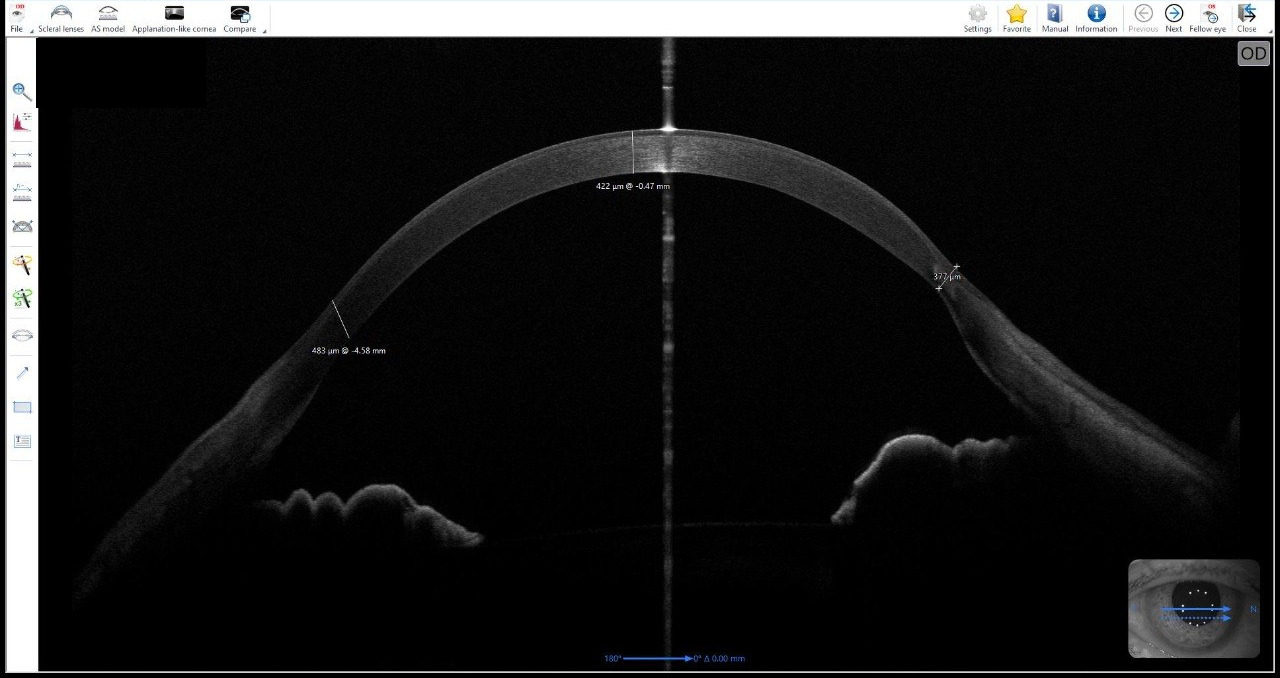
Right eye · AS-OCT
377 µm · peripheral thinning
422 µm @ −0.47 mm
Pachymetry
422 µm
At −0.47 mm from the vertex
Near-central cornea
483 µm
At −4.58 mm from the vertex
Opposite mid-periphery
377 µm
Thinnest peripheral measurement
The band of ectatic thinning
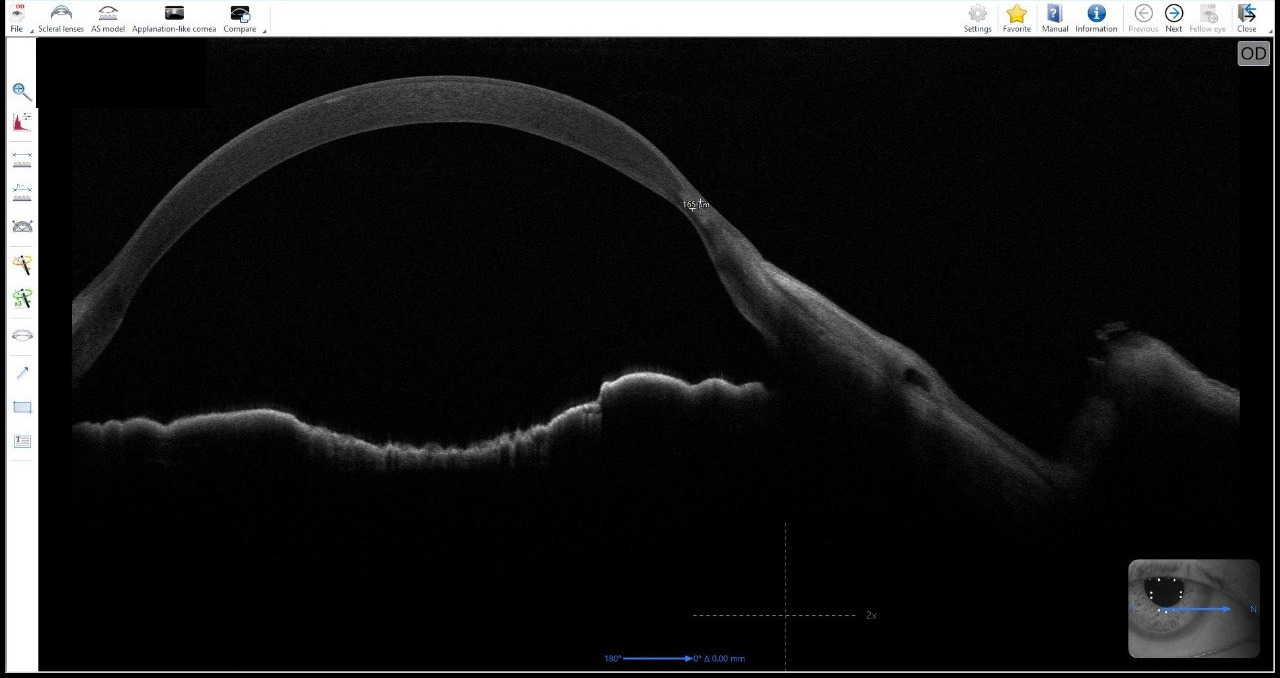
Right eye · 1.65 mm
Peripheral Stromal Thinning with a Preserved CentreInvestigations
13 · Investigations — Left Eye Imaging13 / 23
The same disease, less far along
Left eye · AS-OCT
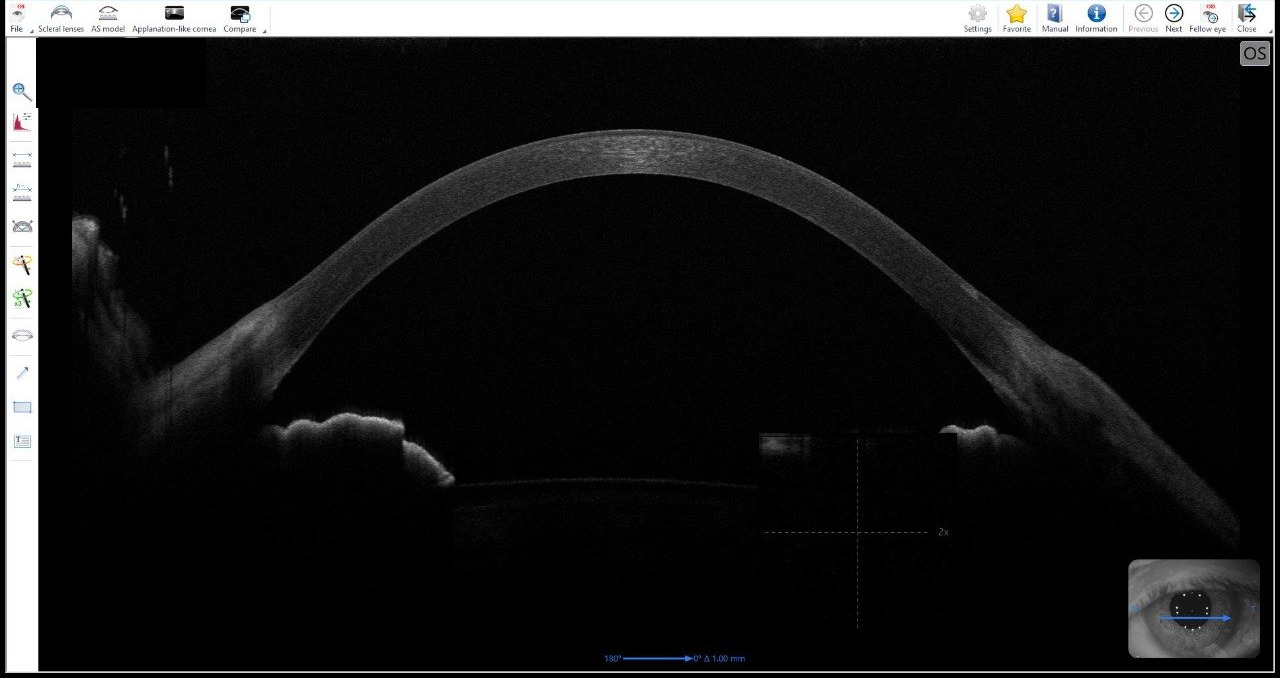
Left eye · Δ 1.00 mm
Radial section of the left cornea — peripheral thinning present but less marked than the right; the centre is preserved.
Left eye · Scheimpflug overview
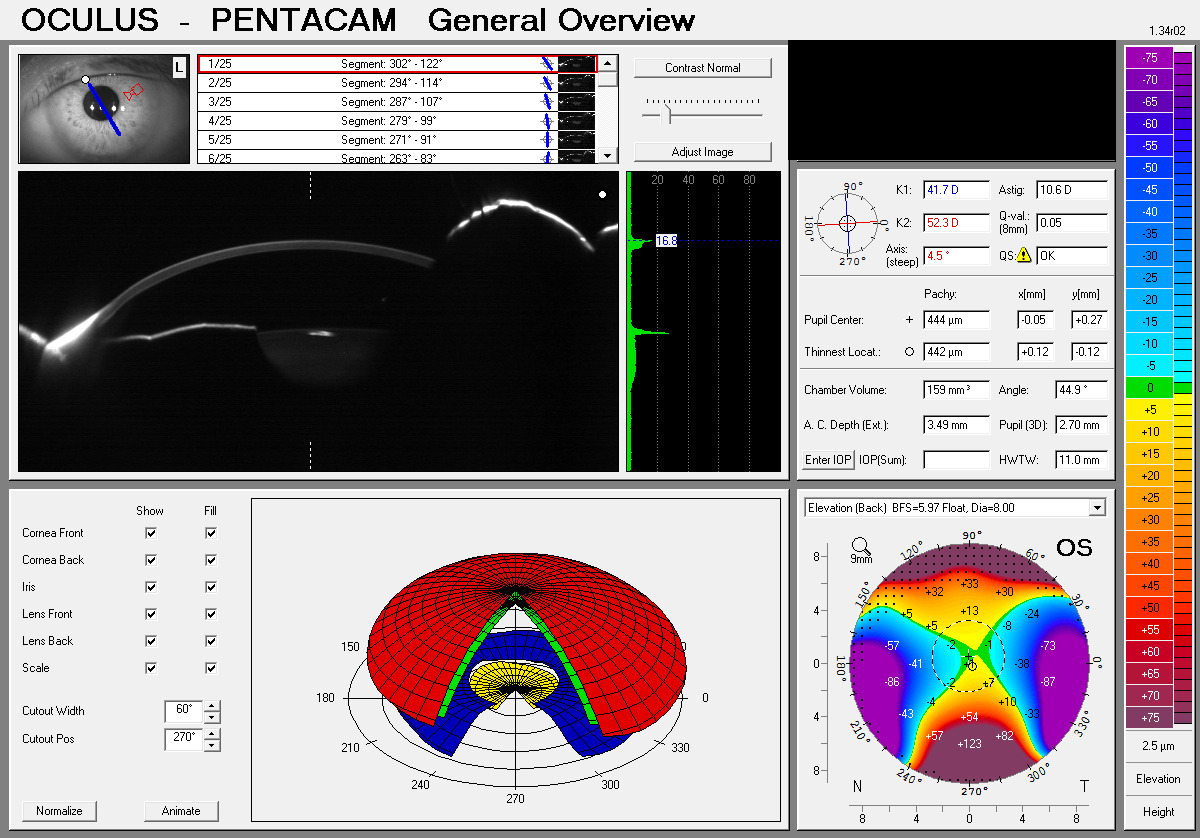
Left eye · Pentacam
Scheimpflug section with densitometry — astigmatism 10.6 D at a steep axis of 4.5°, thinnest location 442 µm.
Left Eye: Same Pattern, Lower MagnitudeInvestigations
14 · Investigations — Scheimpflug Tomography14 / 23
The crab-claw, on four maps
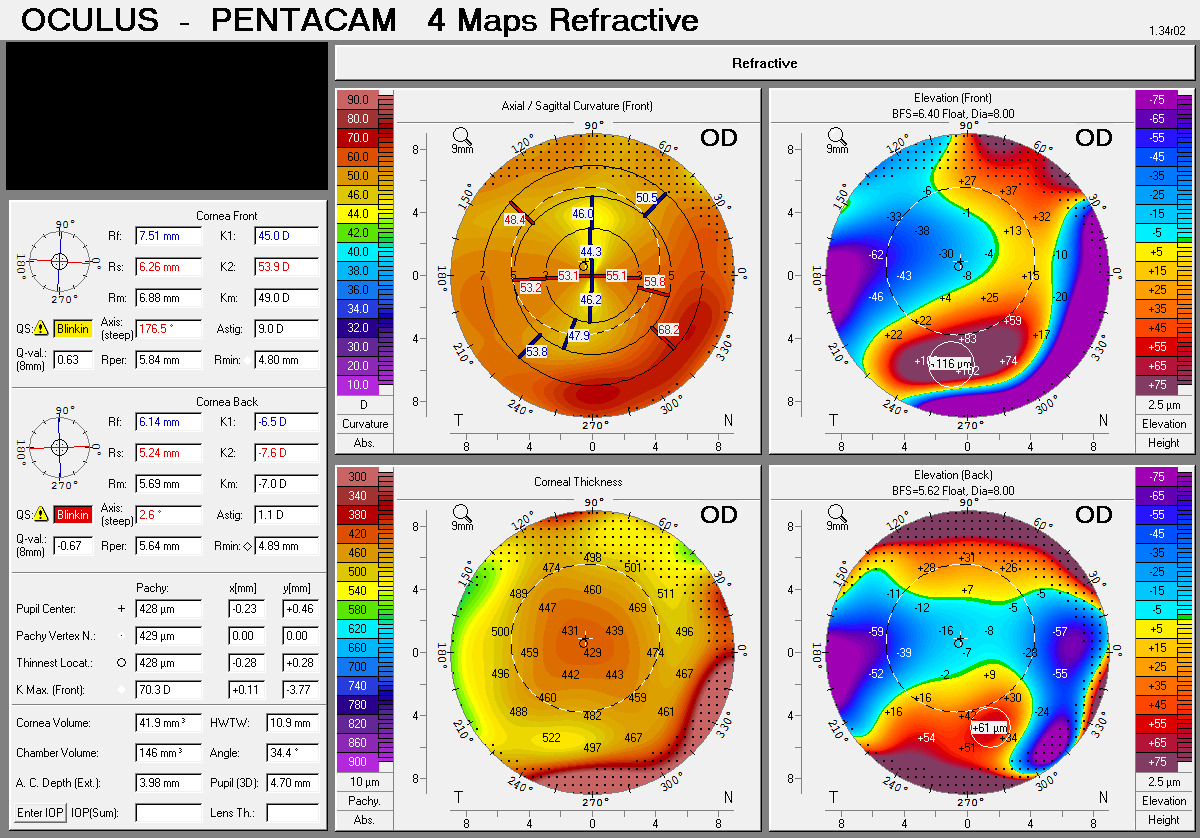
Right eye · 4 Maps Refractive
Right eye · Cornea front
| K1 / K2 | 45.0 D / 53.9 D |
| Km | 49.0 D |
| Astigmatism | 9.0 D · steep axis 176.5° |
| K max (front) | 70.3 D |
| Thinnest location | 428 µm |
| Q-value (8 mm) | 0.63 — oblate |
| ACD / volumes | 3.98 mm · cornea 41.9 mm³ · chamber 146 mm³ |
Inferior steepening with flattening of the vertical meridian — the butterfly of pellucid marginal degeneration, and a K max no keratometer would predict from the refraction.
Tomography Explains What Keratometry CannotInvestigations
15 · Investigations — Belin/Ambrósio Display15 / 23
Ectasia, objectively
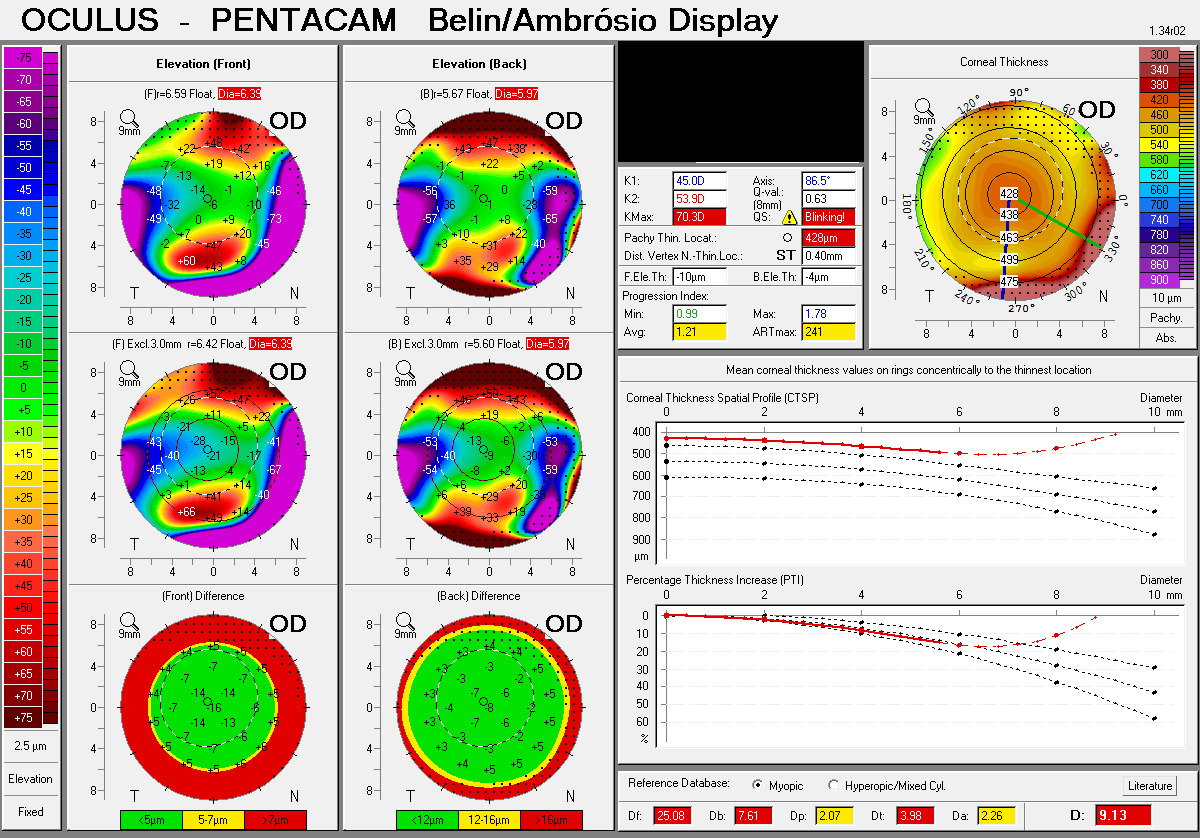
Right eye
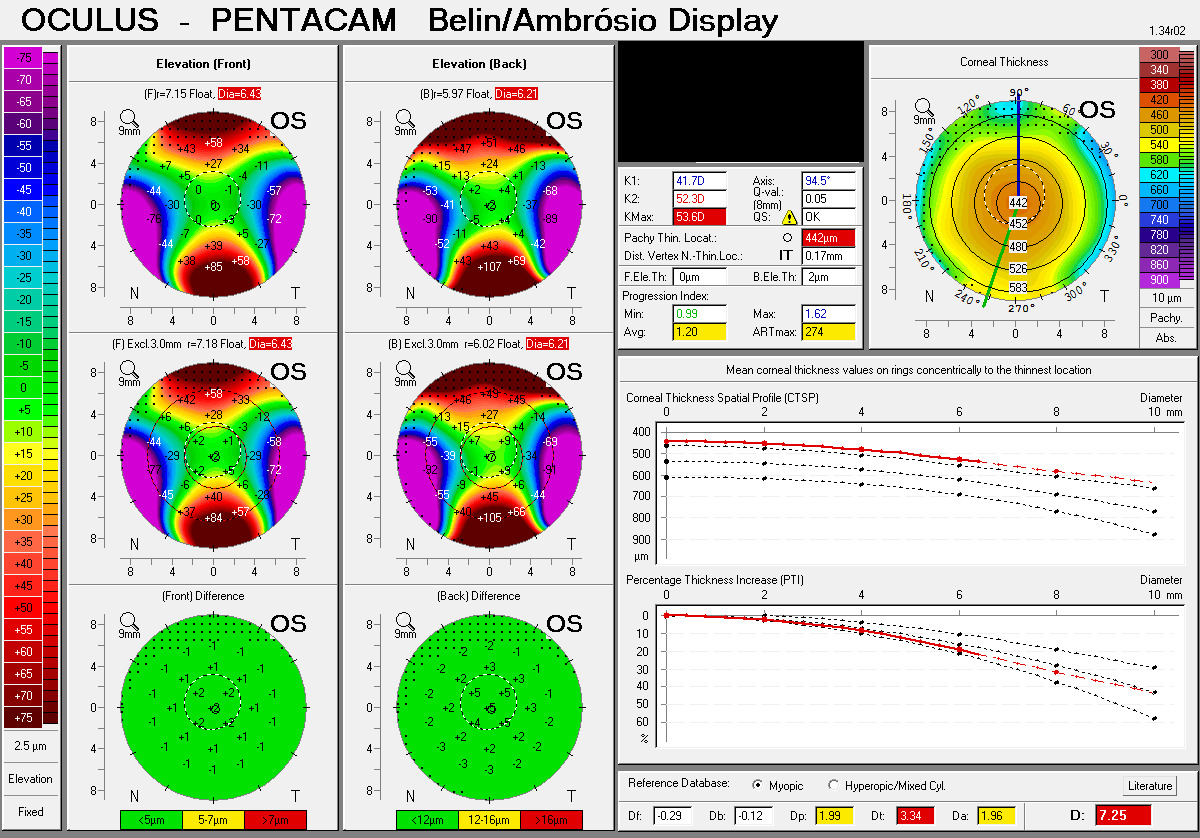
Left eye
9.13
Final D value · right eye
Abnormal beyond 1.6
7.25
Final D value · left eye
Bilateral disease, asymmetric
241 · 274
ART max, right and left
Thinnest point vs progression
428 · 442
Thinnest location, µm
Displaced inferiorly, both eyes
Both Eyes Flagged: Enhanced Ectasia Confirms the DiagnosisInvestigations
16 · Investigations — Biometry & IOL Calculation16 / 23
Where the numbers fight the formula
| Optical biometry | Right eye | Left eye |
|---|---|---|
| Axial length | 26.89 mm | 25.81 mm |
| Flat K (K1) | 44.84 D @ 84° | 41.75 D @ 95° |
| Steep K (K2) | 53.36 D @ 174° | 52.65 D @ 5° |
| ΔK (astigmatism) | +8.51 D @ 174° | +10.90 D @ 5° |
| SE / TSE | 48.73 / 48.84 D | 46.57 / 46.56 D |
| ΔTK (total keratometry) | +8.55 D @ 174° | +11.01 D @ 5° |
| ACD / LT | 3.93 / 3.89 mm | 3.46 / 3.98 mm |
| White-to-white | 11.3 mm | 11.4 mm |
- Steep meridian near-horizontal in both eyes — biometric confirmation of against-the-rule ectatic astigmatism.
- Lens thickness flagged by the biometer in both eyes — consistent with cortical cataract.
- Barrett Universal II used for power selection: monofocal IOL ≈ +3.7 D for emmetropia (RE) and ≈ +8.6 D (LE) — unusually low powers driven by long axial length and steep mean keratometry.
Long Eye + Steep Irregular Cornea = Formula Stress-TestInvestigations
17 · Investigations — IOL Selection17 / 23
Choosing the implant
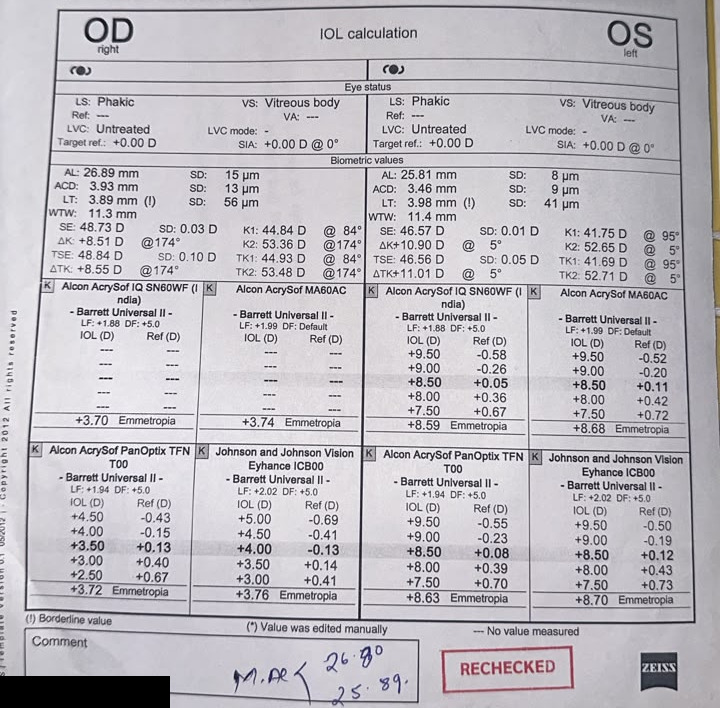
IOL calculation · both eyes
Optical biometry, both eyes — phakic, vitreous body, untreated. The sheet is stamped rechecked, with axial length measured again by hand.
Barrett Universal II · target emmetropia
| Implant option | Right eye | Left eye |
|---|---|---|
| AcrySof IQ SN60WF — emmetropia | +3.70 D | +8.59 D |
| Power selected · predicted | +3.50 D → +0.13 | +8.50 D → +0.11 |
| AcrySof PanOptix TFN T00 — emmetropia | +3.72 D | +8.63 D |
| Power · predicted | +3.50 D → +0.13 | +8.50 D → +0.08 |
| Manual axial length, rechecked | 26.80 mm | 25.89 mm |
Powers this low are driven by a long eye and a steep mean cornea — the two errors push in opposite directions, which is exactly why the sheet was rechecked. The diffractive option was calculated and deliberately not chosen: irregular ectatic astigmatism and multifocal optics do not belong in the same eye.
Monofocal Implant · Barrett Universal II · Conservative TargetInvestigations
18 · Differential Diagnosis18 / 23
Teasing out the thinning cornea
| Considered | Why it was considered | Why it was excluded |
|---|---|---|
| Keratoconus | Ectasia with high astigmatism and progressive myopic shift | Thinning here is peripheral, not apical — protrusion sits above the band; no Fleischer ring, no Vogt striae, no cone on tomography |
| Terrien marginal degeneration | Peripheral thinning with lipid at the leading edge | Terrien is typically superior and vascularised; this band is inferior, avascular, with intact epithelium |
| Keratoglobus | Bilateral thinning with globular steep corneas | Thinning is limbus-to-limbus in keratoglobus; here the central cornea and the limbal margin are spared |
| Mooren / marginal ulcerative keratitis | Peripheral corneal thinning | No pain, no inflammation, no epithelial defect, no infiltrate — a quiet eye over three years |
An inferior crescent of thinning 1 mm inside a clear limbus, steepest cornea above the band, and a crab-claw map — the diagnosis is pellucid marginal degeneration.
Location · Vascularity · Inflammation · TopographyDifferential Diagnosis
19 · Treatment19 / 23
A staged, conservative plan
Step 1 · Optical rehabilitation trial
Spectacle correction inadequate (4/60, 5/60). Semi-scleral contact lens trial improved acuity — confirming the corneal component and establishing the post-operative rehabilitation route.
Step 2 · Cataract surgery, right eye first
Phacoemulsification with in-the-bag monofocal IOL (Barrett Universal II), right eye first as the worse eye; peribulbar anaesthesia with attention to the thinned peripheral cornea during incision planning.
Step 3 · Residual astigmatism managed off the cornea
Irregular ectatic astigmatism to be corrected with a scleral contact lens after surgery, not with a toric or multifocal implant.
Deliberate exclusions
- No multifocal IOL — diffractive optics compound the higher-order aberrations of an irregular cornea.
- No toric IOL — the astigmatism is irregular and potentially progressive; axis determination is unreliable, and a scleral lens would neutralise the front surface anyway.
- No simultaneous corneal procedure — the ectasia was managed conservatively; the cataract is addressed first, the cornea rehabilitated optically.
Phacoemulsification + Monofocal IOL + Scleral Lens RehabilitationTreatment
20 · Outcome and Follow-up20 / 23
Outcome and surveillance
Immediate outcome
- Right eye surgery completed uneventfully under peribulbar anaesthesia; pre-operative fasting and pre-anaesthetic orders followed.
- [Editable] Post-operative day-1 findings: add vision, IOP, wound and IOL status here.
- [Editable] Post-operative refraction and best-corrected acuity at 4–6 weeks: add here.
Planned follow-up
- Scleral contact lens fitting once refraction stabilises; then second-eye surgery.
- Glaucoma surveillance — Humphrey 30-2 fields, disc imaging, IOP review on therapy.
- Ectasia surveillance — serial tomography to document stability of the peripheral thinning.
- Retina review — the myopic chorioretinal degeneration and the flat pigmented lesion (left eye) kept under observation.
Press E to Edit — Add Post-operative Data When AvailableOutcome and Follow-up
21 · Discussion21 / 23
Cataract surgery on an ectatic cornea
- Keratometry misleads. In PMD the measured Ks sample a grossly asymmetric cornea; standard formulas assume regularity. Reported strategies include using flatter or tomography-derived total keratometry, modern formulas (Barrett Universal II), and counselling for refractive surprise.
- Long eyes add error. Axial myopia (26.89 mm here) compounds formula inaccuracy; a slightly myopic target is safer than emmetropic ambition.
- The contact lens trial is diagnostic and prognostic — it separates corneal from lenticular blur and previews the achievable end-point.
- Published experience is sparse. Case reports and small series of cataract surgery in PMD converge on the same choices made here: monofocal implant, astigmatism managed with rigid/scleral lenses, torics reserved for stable, regular-bowtie cases.
- Comorbidity shapes prognosis. Disc asymmetry with a positive glaucoma history and myopic chorioretinal degeneration cap the visual ceiling — honest counselling belongs in the consent discussion.
Formula Choice · Refractive Target · Lens Strategy · CounsellingDiscussion
22 · Learning Points / Take Home Messages22 / 23
What to remember at the slit lamp
- Extreme against-the-rule astigmatism deserves tomography — pellucid marginal degeneration hides behind a “high cylinder” refraction, and the thinning band is easy to miss without a deliberate look at the inferior periphery.
- In ectatic corneas, standard keratometry cannot be trusted for IOL power; use modern formulas, tomography-informed keratometry, and set a conservative, slightly myopic target.
- A rigid or scleral contact lens trial before surgery both proves the corneal contribution to visual loss and predicts the quality of post-operative rehabilitation.
- Monofocal implants are the default in irregular corneas; multifocal optics are best avoided, and toric correction is unreliable when the astigmatism is irregular or progressive.
- Complete the whole examination — coexisting glaucoma suspicion and myopic fundus degeneration change the counselling, the consent, and the follow-up plan.
Five Take-Home MessagesLearning Points
Ophthalmology · Grand Rounds
Clinical Case Presentation
Thank you
Questions & discussion
Bilateral pellucid marginal degeneration with cortical cataract — presented in the structure of a BMJ case report.
Cornea & Cataract Services · Tertiary Eye Care Centre
23 / 23